
Hormonal therapy remains the foundation
Hormonal therapy is still the core of treatment for most people with advanced prostate cancer. Because the cancer often relies on testosterone to grow, lowering testosterone is usually an early goal, typically starting with androgen deprivation therapy after imaging, biopsy, bloodwork and PSA testing clarify the extent of the disease. From there, the path varies: some patients remain stable for long periods, while others need additional therapies much sooner.
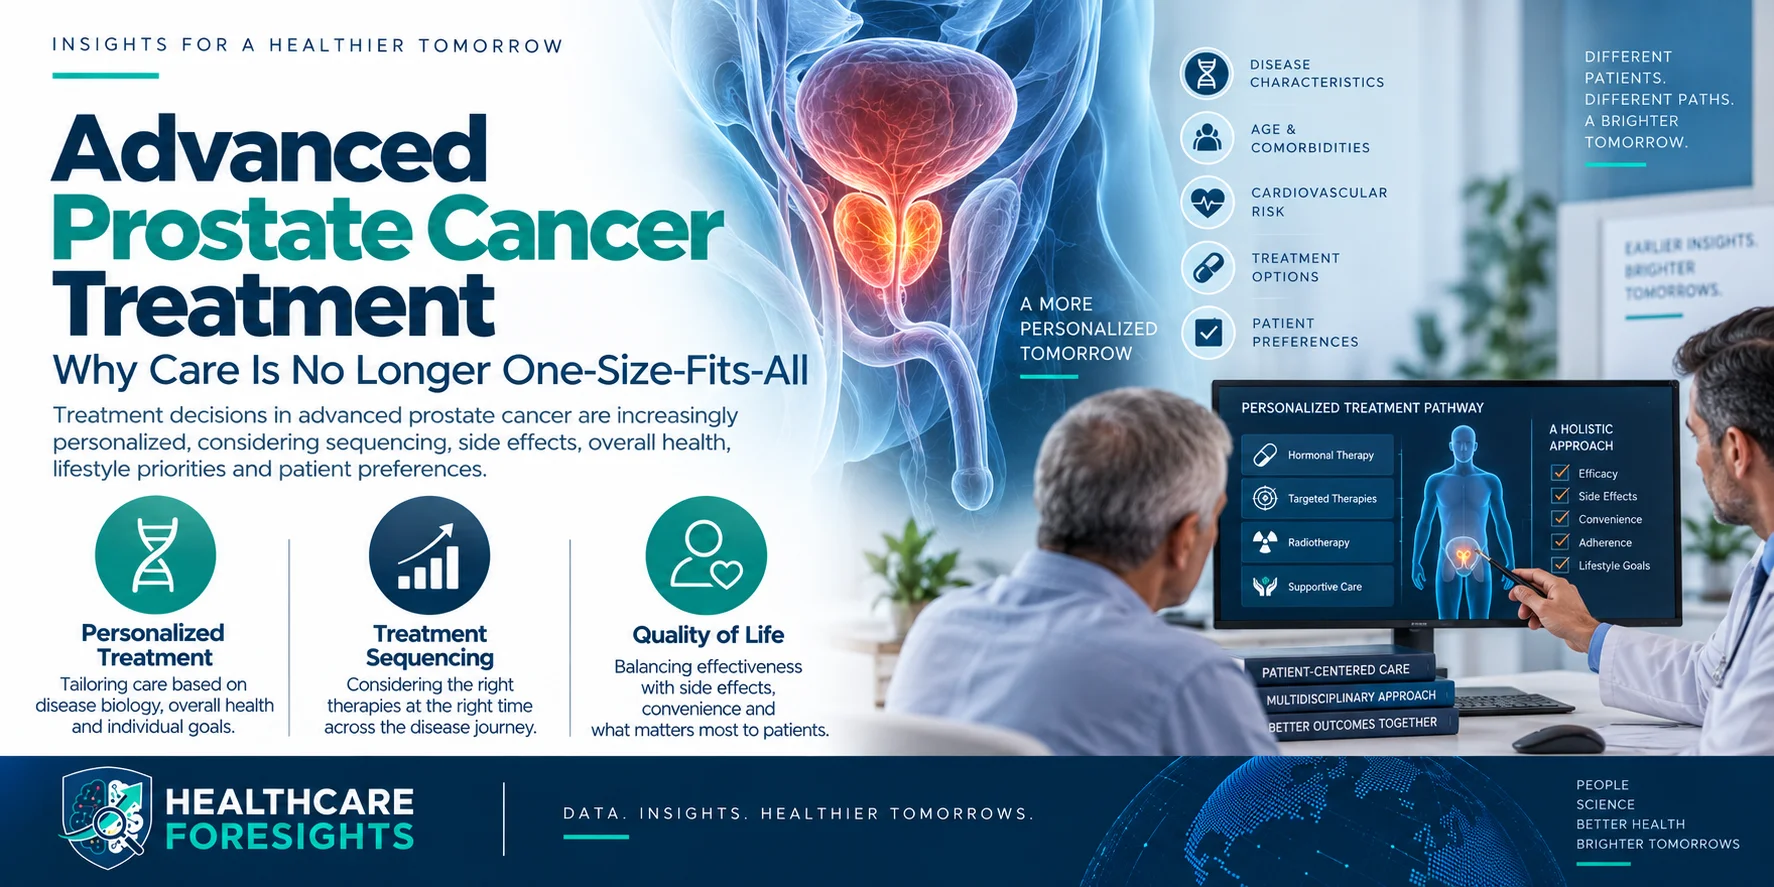
Quality of life is shaping decisions
Patients increasingly want to discuss daily life alongside disease control. Common questions include how often clinic visits will be needed, how severe side effects may be, whether treatment will interfere with work or routine, and how quickly symptoms are likely to improve. These questions matter most for patients who will stay on therapy for extended periods.
Oral GnRH antagonists draw interest
Oral GnRH antagonist therapies came up often. For some patients, a daily tablet is easier to manage than repeated injections or procedures, and the absence of the testosterone flare seen with some older therapies can matter clinically in certain cases. Clinicians caution that convenience depends on adherence and that close monitoring is still needed to confirm treatment is working.
A shift in mindset
The bigger change is in how treatment is approached. Care is becoming less protocol-driven and more individualized, so patients with similar disease profiles may follow different paths based on age, other health conditions, lifestyle priorities and goals.
- Hormonal therapy remains central, but treatment decisions around it have multiplied.
- Sequencing, tolerability, cardiovascular concerns, convenience and patient preference all factor into choices.
- Oral options add flexibility but also require strong adherence and monitoring.